

Kapseln mit verzögerter Freisetzung Und magensaftresistente Kapseln are related but not identical. “Delayed-release” is a broad pharmaceutical category for any design that postpones drug release, while “enteric-coated” refers specifically to a pH-sensitive polymer barrier. In der Praxis, all enteric-coated capsules are delayed-release, but delayed-release products can use other triggers (Zeit, Enzyme, usw.). Manufacturers can achieve delayed release by:
Each route has trade-offs in equipment, Flexibilität, und Komplexität. Zum Beispiel, enteric-coated pellets allow multiple release phases in one capsule, but require precise pellet dosing on the Kapselfüllmaschine. Key production considerations include capsule shell compatibility (Gelatine vs. HPMC), coating adhesion, and fill equipment settings. We compare each approach below to help you select the right strategy for your formulation.

„Delayed-release (DR)” is a general term for any oral dosage form engineered to hold its contents for a period after ingestion. Mit anderen Worten, Es Kontrollen Wann the drug is released. Zum Beispiel, an HPMC (Hydroxypropylmethylcellulose) capsule with an extra-thick wall may dissolve more slowly, delaying the release of its API. The goal is often to reduce stomach irritation or target delivery to a later point in the GI tract.
Ein magensaftresistent beschichtet (Acid-Resistant) capsule is one specific way to achieve delayed release. “Enteric” means intestine. These capsules are given a specialized polymer coating that is insoluble in stomach acid but soluble at higher pH (the small intestine). In der Praxis, the capsule stays intact in the stomach (pH-Wert ~1,5–3,5) and only dissolves when it reaches the small intestine (pH ~6.0–7.5). This precisely controls Wo the drug releases. Magensaftresistente Beschichtungen protect acid-labile drugs (z.B. PPIs like omeprazole) and also protect the stomach lining from irritants (z.B. Aspirin).
Erweiterte Version (IST) Kapseln: Forms that release drug slowly over an extended period (Std.) to maintain steady blood levels. Not the same as delayed release. ER systems (hydrophilic matrices, Osmotische Pumpen, usw.) control the rate of release from the moment of ingestion, rather than imposing an initial lag. Zum Beispiel, an ER capsule might gradually release drug over 8–24 hours. Delayed release simply imposes a delay, whereas extended release modulates release rate (oder beides).
Zusamenfassend, all enteric-coated capsules are delayed-release, but not all delayed-release capsules are enteric-coated. Delayed-release covers any mechanism (thicker shell, polymer matrix, Perlen, usw.) that shifts the release profile. Enteric-coated is the most common method, using pH-dependent coatings. Both ensure drugs aren’t released immediately, but delayed-release focuses on timing, while enteric-coated focuses on bypassing the stomach.
The table below summarizes the major differences between delayed-release and enteric-coated capsules:
| Attribut | Delayed-Release Capsules | Magensaftresistente Kapseln |
| Mechanismus | Zeit- or shell-thickness controlled delay; uses slower-dissolving shell (z.B. HPMC) | pH-triggered polymer barrier; dissolves at intestinal pH |
| Kontrollen | Wann release occurs (lag time) | Wo (in GI tract) release occurs |
| Acid Resistance | Depends on material; typically not specifically acid-resistant unless formulated that way | Engineered for gastric resistance; remains intact in stomach (pH-Wert<5.5) |
| Release Trigger | Intrinsic (mechanical/ time) or enzymatic factors | Alkaline pH (z.B. pH ≥5.5–6.5) in small intestine |
| Anwendungsfälle / Anwendungen | General delayed effect, reduced GI side effects (z.B. Fischöle, reflux-protecting NSAIDs, berberine) | Acid-sensitive APIs or intestine-targeted drugs (z.B. PPIs, pancreatic enzymes, Probiotika) |
| Typical Polymers/ Materials | HPMC- oder Gelatineschalen (thicker or crosslinked); fillers like starch, Zellulose; timed-release beads (z.B. Ethylcellulose) | Enteric polymers: Celluloseacetatphthalat (KAPPE), HPMC phthalate, Eudragit L/S (methacrylates), Schellack; Weichmacher (TEC, phthalates) |
| Release-Profil | Lag phase (often 30–60 min or longer) then rapid release | No release in acid; complete release after pH rise (often 2–4 hrs after dosing) |
| Stabilität | Typically stable; moisture control if using HPMC (geringe Feuchtigkeit) | Stability depends on polymer (some absorb moisture); enteric capsule shells may have low water content (4–10 %). Both need humidity control. |
| Fertigungskomplexität | Moderate – standard capsule filling, no coating step (if using HPMC shells) | Higher – extra steps (polymer mixing, spray coating or specialized shells) |
| Kosten | Mäßig (standard capsule materials) | Höher (enteric polymers and processes add cost) |
| Regulatory/ Tests | Tested with standard dissolution (z.B. USP 711) after lag time | Requires multi-stage testing: disintegration in pH 1.2 (no release), then dissolution at pH 6.8 (freigeben) |
This table captures the core contrasts. Delayed-release “postpones” release based on material and thickness, while enteric capsules add a chemical barrier that only dissolves at intestinal pH. In praktischer Hinsicht, use delayed-release if the goal is Timing (z.B. reduce reflux or provide convenience) and use enteric-coated if the API is acid-sensitive or targeted to the intestines.

At a mechanistic level, delayed-release capsules often rely on the Kapselhülle itself and fillers:
The science: gastric pH (~1–3) keeps the film intact (no release), but once the capsule passes to the small intestine (pH ~6–7), the enteric film swells and dissolves, liberating the drug. Zum Beispiel, omeprazole is formulated as a delayed-release capsule mit magensaftresistente Beschichtung; without the coating it would be destroyed by stomach acid.
Zusammenfassend, delayed-release encapsulates the broad concept (“hold the drug back”), whereas enteric coating is the technology to achieve that for stomach-sensitive cases.
Delayed-Release Capsule Examples: Delayed-release capsules are often used for ingredients that benefit from a lag but are not damaged by acid. Häufige Beispiele sind: Omega-3-Öle or certain botanicals which can cause reflux if released immediately. Some probiotics (acid-tolerant strains) or peptides fall here if you only need to reduce dose frequency or stomach upset. Im Wesentlichen, if the API irritates the stomach (like an NSAID) but isn’t itself acid-sensitive, delayed-release can improve tolerance.
Enteric-Coated Capsule Examples: Enteric-coated capsules are chosen for acid-labile drugs and targeted GI delivery. Classic examples: Protonenpumpenhemmer (Omeprazol, esomeprazole) and other stomach-acid-sensitive drugs, digestive enzymes (z.B. pancrelipase for cystic fibrosis), und Probiotika (so the bacteria survive to the gut). They’re also used for vitamins/herbals when needed (z.B. SAMe supplements) and some rectally-targeted medications. Many OTC aspirin or ibuprofen products have “enteric-coated” versions to protect the stomach lining. Der Schlüssel ist: if your API or ingredient is inactivated or irritating in acid, enteric is the way to go.
Pharmaceutical manufacturers have several routes to create a delayed-release capsule. Below is an overview of four common approaches, from most to least traditional. Each route has a different process flow, equipment need, und Flexibilität:
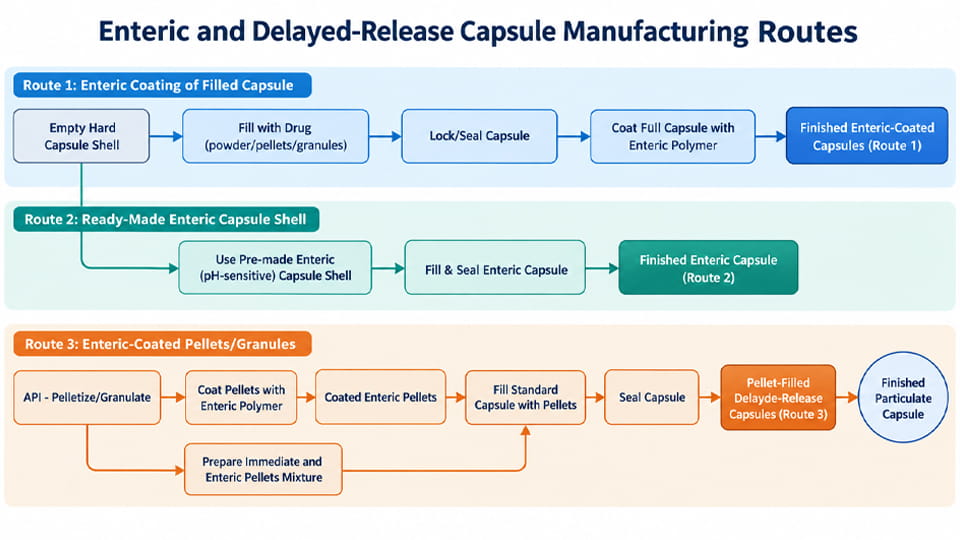
Figur: Four main routes to achieve delayed-release capsules. Route 1 coats the filled capsule; Route 2 uses a ready-to-fill enteric shell; Route 3 fills with enteric-coated pellets; Route 4 (not shown) is a combination of pellets with other formats.
Each route requires appropriate downstream steps. Zum Beispiel, all routes above except Route 2 include a standard capsule locking/finishing step. Routes 1 Und 3 both include a dedicated enteric-coating operation (on capsules or pellets). Route 2 may use a simple sealing machine if special shells come pre-gelled. See the Mermaid chart for flows.

Each piece of equipment must be validated for uniformity. High-shear spray nozzles and precise temperature/humidity control are critical to avoid defects (z.B. “orange peel” surface, knacken).
QC is crucial for both capsule types. Zu den wichtigsten Tests gehören:
According to Kolmar’s overview, “rigorous testing is conducted to ensure each batch meets industry standards for content uniformity, Auflösung, and stability”. In der Praxis, especially for enteric-coated forms, the combined disintegration/dissolution test is paramount.
When scaling production from lab to commercial batches:
Common problems (especially with enteric coatings) enthalten:
Im Allgemeinen, start by examining in-process moisture (too high makes coatings sticky), spray droplet size, and batch-to-batch consistency of excipients. Viele coating defects can be prevented with careful validation and controls.
To decide which is right for your product, halten:
A quick Checkliste:
Choosing early in development is critical. Using the wrong capsule can ruin stability or dissolution and be costly to fix later. Work closely with formulation experts and equipment engineers to make the right call.
Zusammenfassend, verzögerte Veröffentlichung is a broad strategy (any way to postpone release), während magensaftresistente Kapseln are one specific method (acid-resistant film). To design the right delayed-release capsule, first define your release target (z.B. intestinal absorption, Magenschutz) and practical constraints (existing equipment, Formulierungseigenschaften). Then pick a route: coat the filled capsule, use a pH-sensitive shell, fill with coated pellets, or a hybrid approach. Each route will affect your capsule filling process: z.B. pellet fills need pellet-dosing modules, enteric shells require sourcing special capsules, and coated capsules require post-fill coating.
No matter which path you take, remember to test rigorously. Dissolution in acid and buffer, fill-weight uniformity, pellet integrity, and stability are critical checkpoints. Moderne Kapselfüllmaschinen (like JinLu’s automatic capsule fillers) are quite versatile and can handle either route. They support powders, granules and pellets in hard capsules, making implementation feasible on the production floor.
If you’re evaluating delayed-release options for your product, we encourage you to send us your formulation details (Kapselgröße, Material, Fülltyp, Zieldosis, usw.). Our engineering team can then advise which approach fits best and offer sample tests on our equipment. Use the information above to frame your questions, and let us help you choose the safest, most cost-effective manufacturing route for your delayed-release capsules.
Nicht ganz. “Delayed-release” is a general term meaning the drug isn’t released immediately after swallowing. Enteric-coated capsules are one common way to achieve delayed release (by using an acid-resistant coating). So all enteric-coated capsules are delayed-release forms, but delayed-release could also include time-release systems or special multiparticulate designs.
Plain gelatin or standard HPMC capsules dissolve in the stomach and provide immediate release (HPMC may dissolve a bit slower, but still in acid). They have no inherent delay. To achieve delayed release, you need either an enteric coating on the capsule or fill (shell polymers or pellets) that resist acid. Zum Beispiel, Capsugel’s Vcaps® Enteric (HPMC with added polymers) are specially manufactured shells that confer acidity resistance.
Manufacturers can use several routes. They may apply an enteric coating to a filled capsule, use a ready-to-fill functional capsule shell, fill a standard capsule with enteric-coated pellets or granules, or combine coated pellets, Mini-Tabletten, and other fill materials. The best route depends on the required release profile and production setup.
Ja. Hard gelatin capsules can be coated with suitable enteric polymers, but the coating formulation and process conditions must be optimized for adhesion, Kapselintegrität, Feuchtigkeit, Trocknen, and the cap-body joint. The finished product should then be tested to confirm that the required delayed-release or gastro-resistant performance is achieved.
Ja. Filling enteric-coated pellets or granules into standard gelatin or HPMC capsules is a widely used approach for delayed or gastro-resistant drug delivery. In Produktion, manufacturers need to control pellet flow, Dosiergenauigkeit, mechanical handling, and coating damage because excessive abrasion can affect the intended release profile.
Normalerweise ja, but compatibility depends on the capsule shell, Füllmaterial, particle characteristics, Dosis, und Produktionsgeschwindigkeit. An automatic capsule filling machine may require different dosing configurations for powder, Granulat, Pellets, oder Mini-Tabletten. Pellet-filled products also need gentle handling and accurate dosing to protect the functional coating.
Testing normally evaluates whether the dosage form resists the required acidic stage and then releases the drug appropriately under the specified later-stage conditions. Manufacturers may also assess dissolution, Zerfall, coating integrity, fill-weight consistency, Pelletschaden, und Stabilität. The exact acceptance criteria should follow the applicable product specification, pharmacopoeial method, und regulatorische Anforderungen.
Both can become brittle if too dry. Gelatin shells usually have higher moisture, giving them a bit more flexibility (unless exposed to extreme dry conditions). HPMC shells tend to be drier and can crack if mishandled. Monitor humidity during storage and filling. Im Allgemeinen, handle HPMC shells more gently and consider humidifying capsules slightly before filling if brittleness is a concern. Ensure filling machines run under controlled climate (some lines use humidifiers to protect HPMC shells).
Manufacturers should consider capsule size and material, powder or pellet fill type, Dosiergenauigkeit, pellet handling, capsule separation and locking, Produktionskapazität, changeover requirements, Reinigung, und Validierungsunterstützung. For pellet-based delayed-release products, the filling system should be able to dose the pellets consistently without damaging their functional coating.
There are several common approaches: coating the filled capsule with an enteric polymer, using a ready-to-fill enteric-resistant capsule shell, filling standard capsules with enteric-coated pellets or granules, and combining immediate- and delayed-release components in one capsule. The best route depends on the formulation, Ausrüstung, release target, und Produktionsanforderungen.
Referenzen:
1.Oral Gastro-resistant Formulations – State of the Art, Advances and Prospects: A Review —— Springer Natur
2.Fish Oil Containing Omega-3 Acids Delayed-Release Capsules —— USP
3.In-vitro-Bewertung von magensaftresistenten HPMC-Kapseln – Einfluss von Formulierungsfaktoren auf die Produktleistung —— PMC
4.Exploring Immersion Coating as a Cost-Effective Method for Small-Scale Production of Enteric-Coated Gelatin Capsules —— PMC
5.Enteric coated HPMC capsules designed to achieve intestinal targeting —— PMC
6.Guidance for Industry SUPAC-MR: Modified Release Solid Oral Dosage Forms —— UNS. Lebensmittel- und Arzneimittelbehörde



